.jpeg)
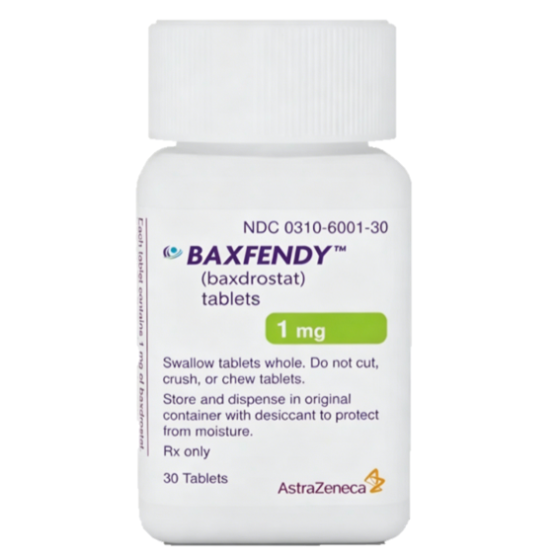
Baxdrostat (Baxfendy) for Hypertension: Aldosterone Synthase Inhibition, Dosing, and Discontinuation Rules
1.Position and Eligible Patients
Baxdrostat(Baxfendy)is an oral aldosterone synthase inhibitor targeting CYP11B2,reducing aldosterone production and thereby decreasing sodium retention,volume load,and blood pressure.It is not a replacement for all conventional antihypertensives but an add-on for adults whose blood pressure remains inadequately controlled with other agents.
Consider it in uncontrolled or resistant hypertension,or when aldosterone pathway involvement is suspected—for example,positive primary aldosteronism workup,low-renin profile,or salt-sensitive patterns—after specialist evaluation.It is not a default first step for mild hypertension or for patients who have not yet optimized standard therapy.
2.Dosing and Administration
Standard:2mg orally once daily;swallow whole with water,do not split,crush,or chew.
High-risk electrolyte groups:older adults,diabetes,chronic kidney disease,concomitant potassium-raising drugs,or abnormal baseline electrolytes may start at 1mg once daily.
Food:with or without meals;fixed timing improves adherence.
Missed dose:take the next scheduled dose at the planned time;do not double.
Combination:use with ACE inhibitors/ARBs,calcium-channel blockers,diuretics,beta-blockers,or other agents per cardiology assessment;do not remove existing antihypertensives on your own.
3.Baseline and Ongoing Monitoring
Baseline:serum potassium,serum sodium,renal function,home/office blood pressure;renin,aldosterone,and primary aldosteronism evaluation when indicated.
During therapy:check potassium and sodium more frequently early and in high-risk patients;elderly,diabetes,CKD,potassium-sparing diuretics,potassium supplements,some ACEIs/ARBs,and NSAIDs require closer surveillance.
Blood pressure:use repeated home and office readings rather than a single normal value;assess orthostatic symptoms.
Interactions:strong or moderate CYP3A inducers may lower baxdrostat exposure and reduce BP control;monitor response more closely and adjust therapy.
4.Safety and Management
Hyperkalemia:key adverse event;roughly 6.6%with 1mg and 10.2%with 2mg in pooled placebo-controlled data.Treat based on severity,hold or stop baxdrostat for significant rises,and consider permanent discontinuation for recurrent clinically important hyperkalemia.Marked hyperkalemia with arrhythmia needs urgent care.
Hyponatremia:more likely with low baseline sodium or risk factors;symptoms include fatigue,nausea,confusion.Correct contributors,hold/reduce dose,and stop for severe cases.
Hypotension/dizziness:common when combined with multiple antihypertensives;assess the entire regimen rather than stopping baxdrostat alone.
Muscle cramps:record frequency and electrolytes;mild cases observe,persistent cases need potassium/sodium/renal review.
Adrenal function:aldosterone suppression does not automatically mean adrenal insufficiency,but if hypotension,hyponatremia,hyperkalemia,or stress intolerance occur with other adrenal-affecting drugs,refer to endocrinology/cardiology.
5.Long-Term Use and Stopping
Baxdrostat lowers blood pressure by continuously inhibiting aldosterone synthesis;after stopping,this pharmacological effect is not permanently retained and blood pressure may rise again.“Long-term treatment”is therefore not“once started,never stop,”but also not“stop once blood pressure normalizes.”
Continue,reduce,or stop based on sustained home/office BP control,existing antihypertensive regimen,lifestyle measures,underlying disease,electrolytes,and renal function.With combination therapy,stopping any single agent can change overall control;all changes should be made by a cardiovascular specialist using home-blood-pressure records and laboratory data.
[ 免责声明 ] 本页面内容来自公开渠道(如FDA官网、Drugs官网、原研药厂官网等),仅供持有医疗专业资质的人员用于医学药学研究参考,不构成任何治疗建议或药品推荐。所涉药品可能未在中国大陆获批上市,不适用于中国境内销售和使用。如需治疗,请咨询正规医疗机构。本站不提供药品销售或代购服务。